Showing posts with label Coronavirus. Show all posts

Thursday, December 15, 2022

The Surveillance File

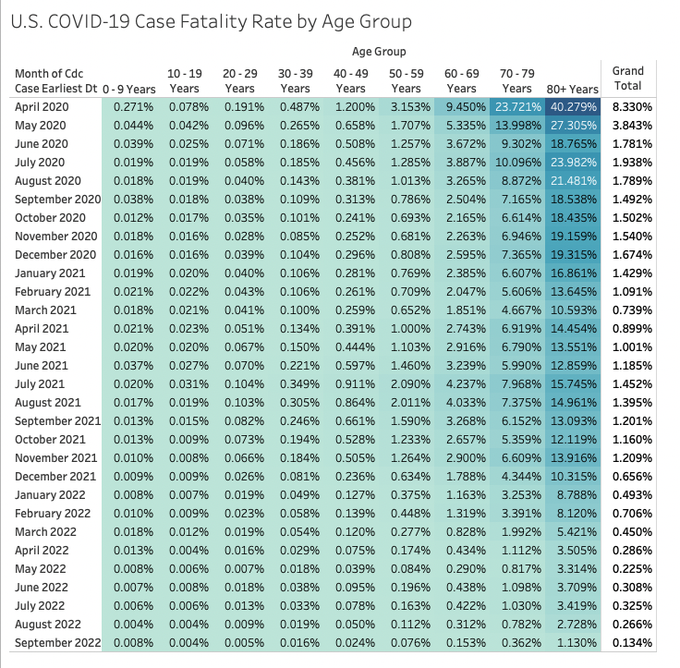
From the CDC Case Surveillance File, some interesting data on Covid mortality rates for various age brackets over the course of the pandemic.  This is the Case Fatality Rate (CFR), individuals specifically diagnosed and reported to authorities.  The CFR is not the Infection Fatality Rate (IFR), which would include all cases and can only be estimated.  The IFR would be substantially lower than the CFR.  For instance, my covid case (which was very mild), diagnosed by a self-administered test while in France this past May, would count under the IFR, but not the CFR, because it was not reported in either France or the United States.

ImageAs you can see, the CFR drops quickly across all age groups after the spring of 2020.  Rates drop throughout 2020, and then drop again in early 2021 as vaccines become available.  There's a further small rise in the summer and early fall of '21 due to the Delta variant and then rates fall rapidly, even for the most vulnerable (those over 80). 

You can easily see the small fatality rate for those under 40, and vanishingly small for those under 20, since the start of the pandemic.  For those 70-79 the CFR has been below 1% since February 2022.  Looking at the data, I think the personal risk assessment I reported on in April 2021 holds up well with one exception.  At the time, it was thought vaccination significantly reduced your chance of infection.  That proved not to be true, though it does reduce the risk of serious consequences.  It's also why it was a mistake to call it a vaccine, when it is closer to a flu shot.

Unless we see a more serious variant develop, covid is now a background risk, mostly for the elderly, just like the flu and pneumonia.

I came across this data after reading an article in today's NY Times on, of all things, the potential for catching Covid from corpses!  The article contained this gem:

"Up to 70 percent of those infected with Ebola die, compared with about 3 percent of those diagnosed with Covid-19."

I thought, am I missing something?  A 3% CFR?  Where'd that come from?  I knew there was a 3.4% fatality estimate based upon early Wuhan data, but wasn't that obsolete?  Well, as you can see it is obsolete.  The last time the CFR in the U.S. was above 3% was in May 2020.  It's been below 2% since then, below 1% since November 2021, and below 0.5% since March 2022 (and for those under 60, the last time above 0.5% was more than a year ago), and as of September 2022 the CFR was less than 1/20 of 3%.

No wonder Times readers are still so freaked out over Covid.  The Times reporting on this, as on many other topics, is no better than watching someone on YouTube promoting ivermectin or telling you that the vaccines contain microchips designed by Bill Gates.

Thursday, August 4, 2022

Have We Learned Anything More?

I've updated my July 14 post on covid origins, Have We Learned Anything?, with additional text, footnotes, and links.  Rather than do a separate new post, I prefer to keep everything relevant to the discussion in one post.  You can find it here.

Thursday, July 14, 2022

Have We Learned Anything?

At least in the case of Covid, probably not.

In October 2021, the United States Agency for International Development (USAID) (1) announced a $125 million, 5 year grant, to Washington State University and partners to find and collect an estimated 8,000 to 12,000 novel viruses existing in the wild, including coronaviruses, "which researchers will then screen and sequence the genomes of the ones that pose the most risk to animal and human health".

I was alerted to this by a recent post from Richard H Ebright, Board of Governors Professor of Chemistry and Chemical Biology at Rutgers, a long time opponent of virus hunting, who only became aware of the grant via a July 5 article in Forbes by Steven Salzberg, Professor of Biomedical Engineering, Computer Science, and Biostatistics at Johns Hopkins, who also opposes such research. 

UPDATE: August 5, 2022  This link takes you to Prof Ebright's Senate testimony on August 3, 2022 in which he explains what gain of function research is, why he opposes it, the failure of NIH to enforce its own guidelines, and how it may be linked to a potential lab leak from the Wuhan lab, the possible origin point for Covid 19.  You can watch the entire hearing with Ebright and two other scientists at this C-Span link.  It is long (1:45) but a very clear and educational discussion by the panelists, making it essential viewing for anyone trying to understand the issue.  It is also very sobering, not just about the potential source of covid-19, but about the larger implications of continued American funding of such research, of which we are the world's leader, and its potential for unleashing an even more deadly pandemic.(2)

Why is this significant?  Because we are still in the midst of a novel-Covid virus pandemic that started in the city which houses the world's largest virology laboratory specializing in finding novel coronaviruses existing in the wild, bringing them back to its lab where it screens and sequences the genomes of the ones that pose the most risk to animal and human health, which it does by, among other things, running them through humanized mice, and where the lab may also have been altering the genomes in unique ways to test their potential human impact.

Two and a half years after the pandemic began there has not been conducted, by China, the U.S., WHO, or by anyone else, a full and transparent investigation into the origins of the pandemic, and key information remains withheld (and possibly destroyed) by China and the United States.

Ebright, Salzberg and others opposed to virus hunting in the wild and gain of function research, believe it highly unlikely that it will provide the benefits its proponents promote, identification, prevention, and development of vaccines in advance; rather that it risks creating the very pandemic it seeks to prevent.  They believe Exhibit 1 is the Covid-19 pandemic, which broke out in the very city where the world's leading research lab on bat viruses is located, yet it was unable to do anything to predict or prevent this very outbreak and, may indeed, have been its very origin.

At a minimum, the U.S. should not be funding any further research of this type until it determines whether the Covid outbreak was of zoonotic origin or via a laboratory leak, and until we have full confidence that such research can be done safely in non-urban locations.  Even with that, I am unpersuaded at this point of the value of such research.

While we desperately need an open investigation into all possibilities, my own views on the origins have changed since early 2020.  At that time, I felt a lab leak was a possible source, but also believed the predominant theory that it was the wet market in Wuhan that was the likely source (including the possibility that a lab tech might have sold an infected animal to someone in the market, which has happened before in China).  Today, my default assumption is the Wuhan Institute of Virology (WIV) was the source via an accidental release.

Back in March 2020, I misunderstood some factual aspects, having heard the WIV was located in Wuhan after the SARS epidemic because it was near the area where infected bats were found, thus facilitating study.  This was incorrect.  The WIV was opened before SARS and the bats it was studying were imported from hundreds of miles away in South China and Southeast Asia.

We also now know that 2 1/2 years after the pandemic began no intermediate host animals, the direct transmittal route to humans, have been identified for the Covid-19 virus.  I was in China just before and just after the SARS outbreak and am well aware that the intermediate host (civets) were identified within two months.(3)

It's also been revealed that U.S. Embassy officials in Beijing who visited the WIV prior to the pandemic were concerned enough about safety issues to prominently raise this in communications.

But there's more, and it goes to the reaction to the outbreak in China and, sadly, in the United States.

In September 2019, the WIV online database went offline.  This database, the largest in the world of coronavirus genomes, had been available to researchers from other countries, including the U.S., which also provided some of WIV's funding.(4)  It has never been restored.  The China government refused to fully cooperate and give open access to the WIV during the WHO investigation in early 2020, and has refused repeated calls to cooperate with any further investigation.  More recently, we've learned that samples taken from early Covid patients in Wuhan, which might shed some light on origins and timing of the outbreak, have been destroyed.  The behavior of the government and associated entities is in marked contrast to what happened with SARS in the early 2000s, and we can make reasonable inferences from this behavior. 

And then there is the role of the United States.

Since 2009, USAID has run an international program called PREDICT, funding projects to identify and analyze wildlife viruses with the potential to cause pandemics, and one of its long-time partners is the EcoHealth Alliance.  Over the years, as virus-hunting has increased under PREDICT,  EcoHealth Alliance has been generously funded to coordinate these efforts internationally.  For the five years prior to the recent announcement of the Washington State grant, EcoHealth had a $62 million contract to undertake similar activities, meaning that the recent grant is not just a continuation but an acceleration of virus-hunting efforts.  EcoHealth Alliance has played a key role because of its advocacy, project leadership and serving as a link between various international organizations, including in the U.S., and the Wuhan Institute of Virology.  In 2016, a parallel international effort, the Global Virome Project (GVP), spearheaded by EcoHealth, was launched to identify all zoonotic viruses with pandemic potential.

In response to FOIA requests since the outbreak of the pandemic, we now have documents showing that the GVP was proceeding quickly and along with funding from NIAID and other sources was also being funded by the Chinese government.  China was also independently funding this research; according to a State Department cable in April 2018:

"Chinese govt funds projects similar to GVP to investigate the background of viruses and bacteria.  This essentially constituted China's own Virome Project . . . The Wuhan Institute of Virology . . . is the forerunner to the Global Virome Project . . . China has expressed interest in building the GVP database.  Other countries . . . are skeptical on whether China could remain transparent as a gatekeeper for this information."

According to the annual PREDICT report in December 2018, the China Virome Project would rollout in 2019-20.

For technical expertise in evaluating projects and contractors, USAID relies on the National Institutes of Health (NIH), and the National Institute of Allergy and Infectious Diseases (NIAID), which is housed within NIH and headed since 1984 by Dr Anthony Fauci, who has been a prominent advocate for virus-hunting and gain of function research.  NIH and NIAID also directly fund research regarding bats and coronaviruses, including grants to WIV.  In addition, DoD is also funding research in this area through its Defense Advanced Research Projects Agency (DARPA).  EcoHealth Alliance has received funding from all of these sources.

Further, in early 2018, EcoHealth Alliance submitted a proposal to DARPA for Project DEFUSE, a name taken from the goal of the project to "defuse the potential for spillover of novel bat-origin high zoonotic-risk SARS-related coronaviruses in Asia".  To do this, field teams would identify and sample bats with potential high risk spillover SARSr-CoVs.  The teams would then "sequence their spike proteins, reverse engineer them to conduct binding assays and insert them into SARSr-CoV backbones (. . . exempt from dual use and gain of function concerns) to infect humanized mice and assess capacity to cause SARS-like disease".
 
Included in the proposal was a plan to insert a furin cleavage site into a bat coronavirus.  In early 2020, when the COVID-19 genome was analyzed a key and distinctive feature was it had a furin cleavage site which enabled the virus to more efficiently bind to and release its genetic material into a human cell, triggering a dispute among virologists as to its origin.

In addition to EcoHealth Alliance as the lead organization (with Dr Peter Daszak, President of EcoHealth as the Principal Investigator for the project), the proposal identifies five other "team members", four of which are located in the United States, the fifth being the Wuhan Institute of Virology.

The proposal was rejected by DARPA.  Among the reasons for rejection were:
 
1.  The proposal is considered to potentially involve GoF/DURC research . . . 
2.  . . . the proposal does not mention of assess potential risks of Gain of Function (GoF) research 
3.  Nor does the proposal mention of assess Dual Use Research of Concern (DURC) issues . . . 
4. The proposal hardly addresses or discusses ethical, legal, and social issues.
Meanwhile, during 2018, the Chinese Academy of Sciences was funding projects at WIV, along the same lines as those proposed in project DEFUSE, and Peter Daszak made continued visits and was in frequent communication with WIV.

What we have in the two years leading to the pandemic is an accelerating effort to identify and manipulate potentially threatening bat viruses at a laboratory in the very city where the outbreak started.

[UPDATE 8/3/22: In a recent article, Alina Chan put it this way:

Disturbingly, documents leaked in September 2021 revealed that Wuhan scientists were part of an international research proposal (from early 2018) that described exactly the type of research that could have created the pandemic virus. Put it this way, it is as if these scientists proposed to put horns on horses and 2 years later a unicorn shows up in their town. When they discover this unicorn and describe it to the public, they talk about every other feature on the creature except for the horn.

Her article, The Evidence For A Natural vs Lab Origin of Covid-19, provides a succinct summary of the argument for both, and why further investigation is necessary.]

Even without China cooperation, there should be a lot of additional data in the hands of the U.S. and EcoHealth Alliance which might shed more insight on origins, but EcoHealth and Peter Daszak have refused to release data in its possession or discuss the matter in public and the U.S. has actively obstructed efforts to use FOIA to get relevant documents released.  What little I have related above, is only known because some information has been pried loose and other have come from leaks inside the agency, but what material has been released under FOIA has been heavily redacted.  This September 2021 article from The Atlantic, discusses some of the government obstruction, and its significance, particularly in regard to the furin cleavage site proposal made in 2018 to DARPA.

And that's even before we get to the events of early 2020.  On January 31, 2020 Dr Kristian Andersen of the Scripps Institute (a NIH and NIAID funding recipient) sent an email to Dr Fauci and others in which he wrote:
Some of the features (potentially) look engineered . . . all [referring to Andersen and other scientists] find the genome inconsistent with expectations from evolutionary theory . . . we have to look at this much more closely and there are still further analyses to be done, so those opinions could still change. 
Over the next four days there was an extensive exchange of emails and a multiparty conference call in which Dr Fauci and Francis Collins (head of NIH) participated.  While we know this occurred, NIH and NIAID have refused to release all but a tiny portion of these conversations.  Then, on February 4 there was a new consensus with Dr Andersen writing an email calling lab origin hypotheses “crackpot theories,” writing, “engineering can mean many things and could be done for basic research or nefarious reasons, but the data conclusively show that neither was done”, followed by a coordinated publicity effort to denounce any proponents of a lab leak as a racist conspiracy theorists, and then a series of articles in prestigious publications like The Lancet proclaiming the virus to clearly be of natural origins.(5)  Many of the virologists signing on to these articles were NIH and/or NIAID grant recipients or had financial ties to EcoHealth Alliance, and it was later revealed Peter Daszak played a key role in coordinating these efforts, though he cleverly avoided having his name attached to them.  For a more detailed explanation of the role of EcoHealth read this Vanity Fair article from March 2022, while this 2021 article in the MIT Technology Review discusses what the WIV may have been up to and the efforts of Dr Fauci to cover any tracks linking his work to the WIV.  For a detailed discussion of the late January/early February 2020 emails see this article in City Journal, by Nicholas Wade.

Peter Daszak has refused all requests to cooperate with congressional inquiries (helped by the fact that the majority party as no interest in such inquiries; for a summary of issues read this letter from House Republican committee members). 

Daszak's evasiveness has been so flagrant that it caused Prof Jeffrey Sachs, the politically progressive scientist from Columbia University, to dissolve the Covid origins panel he was asked to lead by The Lancet. According to Sachs, Daszak, the only American allowed by the China government to participate in the very limited WHO investigation in early 2020, and who was a member of The Lancet panel, refused to cooperate and provide EcoHealth grant documents.  At that point, Sachs recused Daszak from the panel and then, when the EcoHealth documents were leaked and the full extent of Daszak's conflict of interest became apparent, Sachs dissolved the entire panel because he felt its efforts were completely compromised.

These efforts have continued.  In February 2022, the New York Times ran a story on two preprints (non-peer reviewed and yet to be published) articles, one by Dr Andersen, purporting to prove the pandemic started in the Wuhan wet market.  This was part of a media blitz in which, once published by the Times, a paper which combines its own agenda on this with the stunning scientific ignorance of its reporters, it was picked up by many other publications, who went to other virologists primed to give quotes like the preprints had "cracked the case" and "settled" the controversy.  Naturally, the Times article presented no critiques of the preprint, although many soon became available, pointing out the obvious weaknesses in the papers.  I believe the preprints have still never been published in a journal.
 
[UPDATE 8/4/22: The preprints have now passed peer review and been published with much misleading coverage, despite the fact that peer review resulted in the most extreme claims and language in the preprints being modified.  Alina Chan provides a detailed critique in Evidence For A Natural Origin of Covid-19 No Longer Dispositive after Scientific Peer Review, in which she notes:
"After peer review, unscientific language was removed from the Worobey et al. manuscript. However, these strong claims in the preprint had already been widely reported in the media back in February 2022. Needless to say, those journalists likely will not be making corrections or publishing new stories to clarify that these excessive claims have now been eliminated by scientific peer review . . . there are no longer claims of dispositive or incontrovertible evidence in the peer-reviewed paper"
 
"The peer-reviewed paper has an entirely new section on “Study Limitations” which acknowledges that the scientists do not have access to the early Covid-19 case data or locations, lack direct evidence of a market animal infected with the pandemic virus, and lack complete details of how the market had been sampled for the virus."]
In May 2022, Prof Sachs and Prof Neil Harrison (also of Columbia) wrote an article in the Proceedings of the National Academy of Sciences calling on:
. . . US government scientific agencies, most notably the NIH, to support a full, independent, and transparent investigation of the origins of SARS-CoV-2. This should take place, for example, within a tightly focused science-based bipartisan Congressional inquiry with full investigative powers, which would be able to ask important questions—but avoid misguided witch-hunts governed more by politics than by science.
They go on to write:
The investigation into the origin of the virus has been made difficult by the lack of key evidence from the earliest days of the outbreak—there’s no doubt that greater transparency on the part of Chinese authorities would be enormously helpful. Nevertheless, we argue here that there is much important information that can be gleaned from US-based research institutions, information not yet made available for independent, transparent, and scientific scrutiny.
 
Blanket denials from the NIH are no longer good enough. Although the NIH and USAID have strenuously resisted full disclosure of the details of the EHA-WIV-UNC work program, several documents leaked to the public or released through the Freedom of Information Act (FOIA) have raised concerns. These research proposals make clear that the EHA-WIV-UNC collaboration was involved in the collection of a large number of so-far undocumented SARS-like viruses and was engaged in their manipulation within biological safety level (BSL)-2 and BSL-3 laboratory facilities, raising concerns that an airborne virus might have infected a laboratory worker. A variety of scenarios have been discussed by others, including an infection that involved a natural virus collected from the field or perhaps an engineered virus manipulated in one of the laboratories.
The article, which can be found here, goes into great detail on the specific aspects of the Covid-19 genome that raise concerns, and is worth reading in full. 

In an op-ed published a few days later in the Boston Globe, Sachs and Harrison were even more blunt:
The origins of the COVID-19 pandemic remain unknown, but may have had an assist from advanced US biotechnology. We do know this: The National Institutes of Health, which funded a lot of potentially hazardous and under-regulated laboratory manipulation of SARS-like viruses, has been less than transparent. And that’s stating matters politely. The NIH has done its part to throw scientists and the public off track regarding the US-based and funded research.

The fact is that NIH has not told the American people, or the scientific community, what it knows about the origins of SARS-CoV-2. In a conference call call on Feb. 1, 2020, NIH leaders heard top virologists explain why the FCS in SARS-CoV-2 indicated the possibility of laboratory manipulation of the virus. Yet just a few days later, NIH encouraged a team of scientists to prepare a paper declaring a natural origin of the virus. Subsequently, NIH has resisted the release of critical documentation and dragged its feet until forced to make disclosures under Freedom of Information Act lawsuits, often providing only highly redacted materials.
The Biden administration and the scientific community need to do better. What work did NIH, DOD, and other US agencies fund that might have contributed to the emergence of SARS-CoV-2? When did agencies of the USG first learn of the virus? What evidence might there be in the United States in the form of laboratory notes, electronic communications, virus databases, and other troves of information, that can shed light on this matter? Why did some components of the Intelligence Community lean toward a laboratory release as the source of the pandemic?

[UPDATE 8/4/22:  In an interview with Current Affairs (which you should read in its entirety), Professor Sachs elaborates on why an investigation is so needed and his theory as to why it has not yet happened in the United States.  Sachs goes into the details about the controversy over gain of function research and the extensive efforts of American agencies and scientists to block the release of relevant documents and stifle discussion.  

Regarding that research effort:

"The alternative that is the right one to look at is part of a very extensive research program that was underway from 2015 onward, funded by the NIH, by Tony Fauci, in particular NIAID [National Institute of Allergy and Infectious Diseases], and it was to examine the spillover potential of SARS-like viruses. The champions of this research explained in detail their proposals. But after the event, we’d never asked them, “So what were you actually doing? What experiments did you do? What do you know?” We somehow never asked. It was better just to sweep it under the rug, which is what Fauci and the NIH have done up until this point. Maybe they could tell us, “Oh, full exoneration,” but they haven’t told us that at all. They haven’t shown us anything."

"Now, again, let me emphasize, we don’t have definitive evidence of either hypothesis. But what we do have is definitive evidence that officialdom has tried to keep our eyes away from the lab creation hypothesis."

The most interesting things that I got as chair of the Lancet commission came from Freedom of Information Act (FOIA) lawsuits and whistleblower leaks from inside the U.S. government. Isn’t that terrible? NIH was actually asked at one point: give us your research program on SARS-like viruses. And you know what they did? They released the cover page and redacted 290 pages. They gave us a cover page and 290 blank pages! [emphasis added] That’s NIH, for heaven’s sake. That’s not some corporation.

He also goes into more detail as to why he disbanded the task force on Covid origins, which he'd put together in his role running The Lancet's pandemic commission:

I appointed him—this was Peter Daszak—I appointed him to chair the task force of the pandemic commission that I was running for the Lancet. And he headed a task force on the origins. I thought, naively at the beginning, “Well, here’s a guy who is so connected, he would know.” And then I realized he was not telling me the truth. And it took me some months, but the more I saw it, the more I resented it. 

And so I told him, “Look, you have to leave.” And then the other scientists in that task force attacked me for being anti-scientific. And I asked them: “What are your connections with all of this?” They didn’t tell me. Then when the Freedom of Information Act released some of these documents that NIH had been hiding from the public, I saw that people that were attacking me were also part of this thing. So I disbanded that whole task force. So my own experience was to witness close up how they’re not talking. And they’re trying to keep our eyes on something else. And away from even asking the questions that we’re talking about. We don’t have the answers. But we have good reasons to ask. And we have good reasons to know that NIH is not doing its job properly right now.] (6)

So, here we sit in July 2022, with key documents still being withheld by the government agencies which supposedly serve us, while a million Americans are dead and perhaps as many as 20 million worldwide, and with our government funding an expanded virus hunting effort.


Which brings me to Dr Anthony Fauci and his role at NIAID.  Dr Fauci is a 21st century version of J Edgar Hoover and his long reign at the FBI.(7)  I wrote in March:

Once Fauci is gone, I am convinced, if anyone investigates, we will find many scandals at NIAID, just as we did at the FBI after Hoover's death.  Dr Fauci's reign is a prime example of letting an executive run a government agency for decades while escaping accountability.  The doctor last treated patients 51 years ago; has been a senior executive at NIAID for 48 years; and run the agency for the past 38 years.  Every manager in that organization owes their job and their future to Dr Fauci.  Nothing is done without his direct approval or approval by his devotees.  NIAID has a $6 billion budget, a large portion of which goes to funding virology research.  Fauci is the largest funder of such research in the U.S. and possibly the world.  Research careers are dependent upon the doctor's favor.  When Josh Rogin [foreign policy correspondent at the Washington Post] wrote Chaos Under Heaven, his book on the Trump's administration's China policy [for more on this excellent book, read my review], he reported that he was unable to get virologists to speak on the record about Fauci and the origins of Covid because of his control of their funding. (8)

And just like Hoover ran the FBI with an iron fist, involved at every level of decision making, Fauci shares with the former FBI Director a skilled sense of public relations and cultivation of the media, along with a dedicated public fan base that will quickly jump to his defense in response to any perceived challenge to his authority, and like Hoover, Fauci greatly enjoys the publicity and adoration he receives. In Fauci's case, he had the added advantage of establishing his credibility by contrasting himself to the eccentric and ignorant musings of President Trump in their joint press conferences during the early days of Covid.

Dr Fauci position has changed over time from ridiculing any notion of a lab leak origin to, when pressed, tepidly endorsing an investigation of Covid origins but, as the skilled bureaucrat he is, doing nothing to enable such investigation knowing that the current Congressional leadership has absolutely no interest in any investigation that might undermine Dr Fauci's reputation.  The doctor's interest is in smothering any thorough and objective look at this possibility.  Why? (9)

How many virologists are truly convinced that a lab origin hypothesis is not worth investigating?

Can their reasons withstand open inquiry?

Is there a fear that the type of research advocated by the virus hunters could have directly or indirectly led to the pandemic?

Is there a fear that if it did happen, that funding for such research could dry up? 

How has Fauci's control over virology funding impacted the willingness of virologists to speak out?

Maybe some day we will find out.

Could I be wrong with my default assumption about causation?  Sure.  But not about the lab leak being a worthwhile avenue of investigation.

The one thing I am certain of is that the out of hand dismissal of a possible lab leak; when the lab in question was the world largest investigator of bat coronaviruses; where it is possible that research involving the specific characteristics found in the Covid-19 genome may have been conducted; located in the very city where the pandemic began; when no other intermediate source has been identified; and when proponents of the lab leak hypothesis are smeared as racist, conspiracy theorists, is a disgrace to those in the virology community who have propounded this nonsense for the past two years, and yet another example of the self-destruction of our institutions.

-------------------------------------------------------------------

(1) Looking at the USAID press release I was surprised to find the current administrator of the agency is none other than Samantha Power, an outstanding example of a person with certain talents that are a complete mismatch to the government positions she has filled.  Ms Power wrote a fine book, A Problem From Hell: America and the Age of Genocide (2003), about the complexities of dealing with genocidal incidents like the massacre of the Tutsi in Rwanda during the 1990s.  The problems for Ms Power arose when she turned to doing policy and implementation.  She became one of the leading proponents of Responsibility to Protect, which boiled down to a doctrine under which the United States should actively intervene in other countries to protect human rights, but should not intervene to advance its own interests (I'm sure she would rephrase this as "protecting human rights is in American interests, but intervention to protect other U.S. interests bad").  During the Obama administration she served as Senior Director for Multilateral Affairs and Human Rights on the National Security Council and later as Ambassador to the United Nations, where, along with Hillary Clinton she was among the leading voices for the disastrous Western intervention in Libya, where we deposed a deplorable, but under control, dictator who had surrendered his nuclear program, and ended with the chaotic rule of warlords who have caused a decade of civil war, hosted terrorist groups, and triggered a mass migration of illegal immigrants into Europe.

(2) Since everything seems to have a political aspect now, I'll note that all of the Senators asking questions are Republicans.  I do not know the political affiliations of the other two panelists, but having been reading Dr Ebright's twitter feed for several months, it is evident he is a strong Democrat.

(3) In addition to the public release of information during SARS, my work in the safety and health fields put me in touch with China government officials involved with the outbreak and my conversations with them were consistent with the public explanations.  I'll add this was at a time when I was more optimistic about what China's future might be and its relations with the U.S.  Those days are long over.  I also had interesting discussions with officials at the National Development and Reform Commission (then the country's leading policy organization) about climate change and energy, but that's for another day and another post.

(4) This action has raised suspicion that the WIV may have become aware of something going wrong with its lab activities well-before the first reported Covid-19 cases (depending on the source, in either late November or early December).

(5) Even now, it is not uncommon for some to excuse the propaganda campaign by referencing Trump's supposed rhetoric but this gets the timetable wrong.  As Josh Rogin points out in Chaos Under Heaven, the racist conspiracy theory campaign was launched in early February 2020, at a time when Trump was focused on what he thought would be the triumphant announcement of a trade deal with China and he was doing everything he could to placate Xi Jingping and downplaying the covid threat.  It was only in mid-March, after Trump realized Xi was playing him for a patsy that he first referenced the "Wuhan flu" and it was only in mid-April that the administration first spoke publicly about a possible leak at WIV.  Another "fake news" story from this period was Senator Tom Cotton's statement that "We don’t know where it originated, and we have to get to the bottom of that. We also know that just a few miles away from that food market is China’s only biosafety level 4 super laboratory that researches human infectious diseases.”  This was twisted by the NY Times and WaPo into an assertion that China deliberately engineered and released the virus, allowing reporters to denounce it as a racist conspiracy theory.  By the way, we also now know that much of the work at WIV was being conducted at BSL-2, not at the more rigorous BSL-4.

(6) Sachs is director of the Center for Sustainable Development at Columbia University in the US and president of the United Nations’ Sustainable Development Solutions Network.  I am very cautious in dealing with anything from Dr Sachs.  In 2005-6, I attended, as my company's representative, meetings of his climate change group at Columbia's Earth Institute, and heard him expound at length as well as having a couple of brief conversations with him.  I find him to be instantly dismissive of alternative viewpoints and incredibly arrogant, with a firm belief that the most complex problems in our world can be easily solved if only he were put in change with full decision-making authority.  That's been a consistent theme in his career whether it's his economic recovery theories for the former Soviet Union and its satellites in the 1990s or in the failure of the UN Millenium Development Goals in which he was instrumental.  

In this case, everything Sachs is saying that can be verified, I have verified.  For instance, I've seen the FOIA materials that have been released, which include huge amounts of redacted material (I've even looked at the 290 redacted pages describing NIH's SARS research workplan) being withheld in what I believe is blatant violation of the law.  However, keep in mind that Sachs is a consistent critic of America and its foreign policy and most of his criticism around covid is directed at America, not China.  This is perhaps not surprising as he is an advocate of closer ties with China.

(7) Hoover began working at what was then called the Bureau of Investigation in 1921, becoming Director in 1924, a position he maintained until his death in 1972.  Fauci has worked at NIAID for 54 years, three years more than Hoover was at the FBI, though Hoover headed the agency for a decade longer than Fauci.  At least, so far.

(8) Rereading this last sentence it is not as clear as I should have been.  Rogin stated he was unable to get any virologist to speak on the record, and most refused to even comment off the record.  The few who spoke off the record limited their comments to pointing out that Fauci controls the funding in the field.

(9) There are aspects of the Covid origin story that remind me of an incident that started in 1979.  In that year an anthrax outbreak occurred in Sverdlovsk, Soviet Union in which 65 people died.  Soviet authorities blamed the outbreak on the consumption of tainted meat.  There were suspicions in the U.S. about the outbreak as Sverdlovsk was a closed city and major production center for the Soviet military-industrial complex.  It also, as it turned out, housed the Scientific-Research Institute of Bacterial Vaccine Preparations, given that name in 1974, a facility which started in the late 1940s as a biological warfare plant.

In 1972, the United States and the Soviet Union, along with 20 other countries, agreed to the Biological Weapons Convention (BWC) banning biological and toxic weapons by prohibiting their development, production, acquisition, transfer, stockpiling and use.  There are now 184 signatories to the BWC.

During the 1980s there was a growing controversy over the Sverdlovsk outbreak, with the Reagan Administration taking the position that the likely source was the former bioweapons facility, while other prominent figures in the U.S. accepted the Soviet explanation of tainted meat and I still remember the debate. Among these was Dr Matthew Meselson of Harvard University.  Professor Meselson is a renowned geneticist and molecular biologist, who since the early 1960s played a prominent role in advocating for biological and chemical weapons controls.  His reputation was such that he was brought in to help convince President Nixon to sign the Biological Weapons Convention.

In 1979, Meselson was asked by the CIA to evaluate the Soviet claim and he concurred with the tainted meat explanation.  Seven years later he was allowed by Soviet authorities to visit Sverdlovsk and conduct interviews and again concluded that the tainted meat theory was the most likely explanation.

From everything I saw at the time, and have read, since I believe Dr Meselson is a person of high integrity (I do not hold the same opinion of Dr Fauci, nor were the funding, financial, and career conflict issues present in the Sverdlovsk incident) but there was also a political context to the controversy.  Many opponents of President Reagan were fearful that his confrontation with the Soviet Union would lead to disaster and wanted to defuse any possible triggers to such an outcome and were willing to grant the Soviets more credibility in that regard.  Dr Meselson and others also had a great interest in demonstrating the viability of biological weapons controls.  The result was Reagan was often portrayed as a fearmonger and ideologue, with the result, as in many of the disputes of this type, with everyone aligning with their preferred positions.

For whatever reason, Dr Meselson's conclusions, which carried a great deal of weight, particularly with the opponents of Reagan and the media, were incorrect.  After the dissolution of the Soviet Union in 1991, Meselson returned to Sverdlovsk where he had full access to people and documents and concluded that the 1979 outbreak was due to an accidental release of anthrax from a Soviet biological weapons facility.

It turned out the Soviet Union, in violation of the BWC, had a large biological weapons program, which actually expanded under Gorbachev in the 1980s.  Soviet scientists who expressed misgivings about the program were assured that it was necessary since the U.S. was also violating the BWC.  In reality, the U.S. had shut down its programs after signing the BWC.  Within the Nixon Administration there had been a lot of opposition to signing the convention, but when opponents met with President Nixon, complaining that if the Soviets attacked the U.S. with biological weapons we would be unable to respond in a similar way, Nixon simply said, "Well, we'll just nuke them".
Friday, March 18, 2022

19 Notes

. . . on Covid

1.  The worst current covid outbreaks are in East Asia and, of these, the worst is Hong Kong, which had previously managed quite well, relying up strict immigration requirements and quarantine measures.  To my surprise, however, the elderly vaccination rate was quite low so when Omicron hit it took quite a toll.  Currently, Hong Kong is having the US per capita equivalent of over a million cases a day and 11,000 deaths daily.

2.  It is reported that the Hong Kong outbreak has spread to China, and major cities are closing schools and imposing quarantine measures.  This inevitably means further supply chain disruptions between China and the rest of the world.  Adding this to the existing covid induced supply chain disruption along with the more recent Russia-Ukraine war disruption, means we are all in for even rougher times.

3.  Official reported global death toll from covid is a little over 6 million, but it may actually be as high as 18 million.  It is very difficult to make cross country comparisons because of this.  I can tell you there are now 45 countries or jurisdictions reporting death counts in excess of 2,000 per million population, and the U.S. is #18, but I cannot with confidence tell you whether that ranking is correct, or whether other countries reporting less than 2,000, actually exceed this threshold.

4.  Example 1 of the difficulty even in the U.S of making comparisons.  It turns out that states are using different definitions of covid deaths.  Massachusetts has just announced it is revising its definition.  The state had defined as a covid death, any death where covid was listed as one of the causes on the death certificate, or where the deceased had been diagnosed with covid at any point within 60 days of their death.  Massachusetts revised the latter criteria to only include deaths where covid was diagnosed with 30 days of date of death.  The state is imposing this retroactively, which will reduce its previously reported death toll by 15%.

5.  Example 2 of the difficulty in making state comparisons.  Comparisons of raw, unadjusted data can be misleading, particularly if average age is not accounted for because of the relative severity of the disease on the elderly.  If you look at Arizona and its neighbor state, New Mexico, Arizona's death rate is 15% higher, but if adjusted for age the difference is 2%.  Unadjusted v adjusted data is even more dramatic in other instances.  Florida's death rate is 50% higher than California's, but Florida has the second oldest population in the country (Maine is the oldest), while California has a much younger population profile.  Adjusted for age, Florida still has a higher rate, but it is 4% instead of 50% (as of mid-February).

6.  There are also many other population and geographical characteristics that may play a role in the results.  It would be good to explore these in a data drive analysis.  For instance, I mentioned that Maine has the oldest population in the U.S., yet its unadjusted death rate is one of the lowest.  For that matter, the three northern tier New England states all had relatively low death rates.  

7.  It would be useful to get more detailed analysis on international comparisons to see if we can find anything useful for us in America.  For instance, the Netherlands death rate/official case is only 0.3% and its per capita rate less than half the U.S., even though its per capita case rate is higher.  Why?  Are they counting differently?  Are their demographic differences?  Are they treating the infected differently?  I wish there were more reporting.

8. Why did public health officials fail to place a big emphasis on actions people could take to protect themselves in addition to masking (let's put the debate over effectiveness to the side for now), distancing, and vaccines?  It was obvious early on that emphasizing losing weight, exercise, getting outdoors, working to keep medical conditions such as diabetes and high blood pressure under control, Vitamin D levels, were all important to reducing the risk of serious outcomes, yet these were mostly ignored.  Why?

9. The vaccines were oversold as preventing covid infection and that damaged the credibility of vaccination efforts.  However, they were, and remain, effective in reducing the risk of serious consequences if you get covid.  If you are old folks like us, or a younger person with underlying conditions like diabetes, immune system dysfunction, untreated high blood pressure, or seriously overweight, getting vaccinated and boosted is the most effective strategy you can have.

10. Further to #9, I am tired of reading attacks on vaccines by those who deliberately focus on cases and ignore adverse outcomes.  We can directly see the difference in the Omicron surge in East Asia and Oceania.  Hong Kong, Singapore and New Zealand have all seen huge surges in cases but, of the three, only Hong Kong has seen a surge in fatalities because of its low vaccination rate among the elderly.

11.  I'm also tired of arguments by advocates who focus on U.S. data and ignore the rest of the world when it suits their needs, and then turn around and use international data when it does suit their needs.  Or, for that matter, those who selectively use international data, ignoring any that contradicts their argument.

12.  Closing many schools in 2020-21 was a disaster.  Polling indicates most Americans significant overestimate covid risk for children.  It is thankfully very, very small.  We should not repeat this when we have the inevitable covid waves in the future.

13.  Europe took a very different approach to both keeping schools open and masking for children under 12.  Studies found no adverse impacts from the European approach.

14.  Fitted N95 masks can be effective in preventing infection.  Non-fitted, non-certified N95s can be sometimes effective.  Cloth and surgical masks have very little utility.  In the latter case, if those who wear cloth and surgical masks tend to keep more distance from others and to isolate themselves more frequently that may have benefits in reducing infection.

15.  Even before Covid it was apparent the CDC was a troubled organization.  Its mission had expanded and focus drifted from its original task regarding infectious diseases, in part because of Congressional mandates, in part because of the increasing ideological preoccupations of the public health field.  But its incompetence during Covid has been staggering.  I thought Trump's CDC Director, Dr Redfield, was bad, but Dr Walensky, Biden's appointee, has been even worse, sounding panicked, sending conflicting messages, and promoting unsound studies.  Under this administration, the teacher's union president, Randi Weingarten, actually runs Covid policy so perhaps it would have been better to just appoint her.  Congress needs to reform the CDC and return it to its original sole mission regarding infectious diseases.  Of course, it won't.

16.  We still don't know how Covid-19 originated.  I think it was an accidental lab leak in Wuhan but both the lab leak and natural origins need to be properly investigated which has not been done.  China will never cooperate, but there is a lot of additional information available in the United States which is obtainable if Congress took action.  Both the NIH and NIAID (Dr Fauci's agency) have obstructed efforts to FOIA information and the EcoHealth Alliance (funded, in part, by NIH and DoD, has refused to make public documents which could clarify its role with the Wuhan lab.

17.  Will anyone have the courage to force Dr Fauci out of government?  During the early phase of the pandemic the doctor had the advantage of contrasting himself with the random musings of Donald Trump.  Of course, even Andrew Cuomo looked good compared to Trump because, unlike Trump, he could fake empathy even as he massacred nursing home patients.  Fauci's deliberate obstruction of the origins investigation, along with his role in labeling it a racist conspiracy theory, was prompted by his fear that his funding of projects to bring bat viruses to Wuhan may have been linked to the start of the pandemic.  His actions are a disgrace and deserve condemnation.

18.  Once Fauci is gone, I am convinced, if anyone investigates, we will find many scandals at NIAID, just as we did at the FBI after Hoover's death.  Dr Fauci's reign is a prime example of letting an executive run a government agency for decades while escaping accountability.  The doctor last treated patients 51 years ago; has been a senior executive at NIAID for 48 years; and run the agency for the past 38 years.  Every manager in that organization owes their job and their future to Dr Fauci.  Nothing is done without his direct approval or approval by his devotees.  NIAID has a $6 billion budget, a large portion of which goes to funding virology research.  Fauci is the largest funder of such research in the U.S. and possibly the world.  Research careers are dependent upon the doctor's favor.  When Josh Rogin wrote Chaos Under Heaven, his book on the Trump's administration's China policy, he reported that he was unable to get virologists to speak on the record about Fauci and the origins of Covid because of his control of their funding.  Reportedly, over the course of his career, Fauci several times turned down potential nominations to head NIH.  That's because he is a very astute bureaucrat.  He already controlled a large budget and bureaucracy at NIAID, an organization embedded within NIH.  Why heighten his profile, increase his risk of accountability and have to learn and control an even larger bureaucracy when his current position insulated him from all of that?

19.  When is the next variant and what will be its impact?  More importantly, how will we react?

Thursday, January 13, 2022

Metrics

Running a corporate metrics program for environmental and safety performance for a dozen years taught me a few lessons and following covid metrics for the past two years has reminded me of those days.

There are a number of factors important in designing and operating a metrics system.  Here are a few off the top of my head.  I'm sure I'm forgetting a few (age, you know).

1.   What is it you are trying to measure? 

2.   Are there alternative measures that might be more effective?

3.   Why are you trying to measure it? 

4.   What is the value of collecting the data versus the collective effort needed to collect it?

5.   How difficult is it to measure accurately?

6.   How can you validate the metrics being reported to you for accuracy?

7.   What is the criteria for accuracy?  Is close, good enough?

8.   Who will be the customers of that data?  Different customers may use it for different purposes.

9.   Are there desirable behaviors you trying to drive with the metric?

10.  Could you drive undesirable behaviors or create unintended consequences with the metric?

11.  Are you periodically reviewing metrics to make sure they are still necessary and driving the right behavior?

There are two other basic concepts to keep in mind anytime you are measuring and comparing performance on a metric:

Are you using the same measuring stick in all your operations and are others doing the same?

For instance, in the case of covid, is everyone using the same definition of "covid death"?  If not, comparisons become difficult.

Note: Even if it is not the "right" metric if all are using the same measuring stick you can still make useful comparisons.

Even if you are nominally using the same measuring stick is everyone counting accurately?  

In the case of international covid comparisons, some countries may have deficiencies in their health care and data collection systems that make accurate counting difficult, while others may be deliberating manipulating the data.  The global measurement problems with covid are way beyond anything I encountered in the corporate world; The Economist estimates the actual death toll may be up to 3X the current officially reported 5.5 million.

Which brings me to the U.S. metrics around Covid, a situation that has always presented challenges but is becoming even more difficult with Omicron. 

Since the start of the pandemic the states have been reporting Covid hospitalizations.  Under the CDC definition these include all those admitted, for whatever reason, who are found to have Covid.  This is a useful metric in gauging how widespread the pandemic is.  However, it does not tell you how many patients have been admitted because of Covid which would also be a useful figure, particularly for the public.  In my opinion, both types of hospitalization data should have been reported.

This information has been difficult to find.  Over a year ago, I did some research and concluded that about 30% of Covid hospitalizations were for reasons other than Covid.  Subsequent studies indicated that, for children, about 40% of such hospitalizations were for reasons other than Covid, a finding that makes sense given children have less serious Covid health outcomes than adults.

Because Omicron is so easily transmissible, the number of cases has increased very quickly and I would expect the number of hospitalizations with covid to increase substantially but the data I've seen from various hospitals and areas in the U.S. and elsewhere is that up to 70% of those hospitalizations are not because of covid.

The scale and pace of the increase is enormous.  Globally, the 7 day average pre-Omicron was about 490,000 cases (with the pandemic high being 826,000) while it is now 2,647,000 (source: Worldometer).  For the U.S. in early December the 7 day average was 71,000 (with the high in early 2021 at 251,000) ; it now stands at 789,000.  It's probably a good starting assumption now that anyone admitted to the hospital for any reason is very likely to have covid, or to get it while hospitalized.

Another complicating factor is that much of the Northeast, Midwest, and Southwest were still in the Delta wave when Omicron hit and since hospitalizations and deaths lag cases by 2-4 weeks it is difficult to distinguish between the two in the metrics (although individual studies have affirmed that outcomes are significantly better for Omicron).  In the case of Arizona, the case and testing positivity data show that Omicron hit us the week of December 27 which means hospitalization and, more importantly, mortality data is probably still predominantly Delta related.

This also means that covid deaths may become harder to assess.  To be precise, because so many of those hospitalized and in ICUs will have covid, determining whether covid is actually the factor, or a contributing factor to those deaths will become more difficult and I think there will be more people in that category.  Since those dying with a positive covid test are most likely being added into the death count, we may see a duplication of the confusion between dying with or because of that we've seen with hospitalizations.  As it stands, with the current definition probably around 20-25% of covid deaths are with covid.  Many countries other than the U.S., such as the UK and Germany, also use the same reporting standards.(1)

In the near-term I think this issue with how we report the metrics will make it more difficult to determine what is actually happening on a daily basis and will add to public confusion.

In any event, if you're old folks like us, or have risky health conditions, get vaccinated, including your boosters.  Though we've discovered it will not prevent infection as we originally thought, it still greatly reduces your chances of bad outcomes.  Of that there is no doubt.

-------------------------------------------------------------------------------------------------

(1) While there is some uncertainty in calculating covid deaths because of v with, I wanted make sure my views are clear.  Since early in the pandemic I've seen claims that most covid deaths are with, not because of covid.  This is false - I've never been able to confirm any such claims.  Also, whatever uncertainties there are about the covid metrics, it turns out that flu metrics (to which people minimizing the risks of covid like to make comparisons) are even more uncertain and, in my view, more likely to be too high than covid metrics as I discovered looking at the CDC flu methodology back in April 2020.

Friday, October 22, 2021

Modified Limited Hangout

 In an October 20 letter to Congress, the National Institutes of Health grudgingly admitted it funded gain of function experiments at the Wuhan lab but claimed it had nothing to do with Covid-19; a fine example of a Modified Limited Hangout (admitting some of the truth while still managing to withhold the key and damaging facts in the case).

Bottom line is Anthony Fauci and segments of the virology community thought the best way to prevent a pandemic was to find novel coronaviruses in bat caves, bring them hundred of miles to a lab in a city of 11 million people, and enhance them to increase their infectiousness and virulence to humans.  And then they covered it up when it backfired.

When the Obama administration banned gain of function research in 2014 it unfortunately turned over the task of establishing the development of detailed guidelines, monitoring, and reviewing projects to Anthony Fauci.  Bureaucratically this was understandable, since NIAID was the natural spot for the task, but it enabled Fauci, who wanted to continue the research (and still does!), to write guidelines and implement them in such as way as to not impede the projects he wanted to proceed.(1)

Fauci is the 21st century version of J Edgar Hoover, a career bureaucrat (he’s headed NIAID since 1984, held senior positions there since 1974 and started working at the agency in 1968 – and his wife is head of the Bioethics Dept of the National Institutes of Health of which NIAID is a part).  He’s accumulated enormous power and prestige, has very little oversight, loves publicity, manages the media well, and has a cult following that will turn on anyone who attacks him.

Josh Rogin, who wrote Chaos Under Heaven, a very good account of China policy in the Trump administration (about which I plan to write more) which concludes with the Covid pandemic, reported that when he tried to talk to researchers about Fauci they would not go on the record with criticisms because he controlled so much of their funding.

The problems with this research and the response of Fauci and the virology community are multiple.

Should it be occurring at all, given the risk?

If the research should be done, why is the U.S. government funding a lab in the middle of a metropolitan area in China to do it?  Particularly with the lack of transparency and outright deception by both the lab and the China government.  And co-located with Chinese military labs conducting biological research!

Why is the EcoHealth Alliance still receiving U.S. funding (and not just from NIH, it also gets DoD grants), when it has deceived the public and now the U.S. government also admits being deceived by EcoHealth?

Why has NIH refused to release to Congress the details on its funding of projects at the Wuhan lab?

And read Alina Chan on twitter, for calm, thorough and knowledgeable analysis of all this.

----------------------------------------------------

(1)  I've been doing additional research and finding a lack of clarity around Fauci's specific role (was it direct or indirect?), and around key definitions.  That he manipulated the process and worked around the end result is clear, but it is less clear to me how he did it.

Sunday, September 26, 2021

COVID + 18

This is going to be my last monthly Covid update, though I may do occasional posts on specific aspects.

The Delta wave which severely impacted South and Southeast Asia seems to be receding, as it is in most of Latin America, except perhaps Mexico.  In Europe it has now spread to some of the countries in the east.  The Africa data remains difficult to interpret.

The situation in the U.S. is mixed.  Overall cases are down by about 20% in the past couple of weeks but deaths have not declined.  If cases continue to decline we'd expect deaths to start doing the same over the next 10-14 days.  However, the U.S. also has confounding factors, including geography, what appears to be seasonal patterns, and differing vaccination rates, so whether the current trends continue is in question.

Last year we had patterns where the southern states had a summer wave, followed by the upper midwest and then the northeast over the winter.  Will it repeat or will Delta moderate when it gets to the most vaccinated states?  We are already seeing some increase as it moves north.  An anomaly is what Florida experienced, compared to states like Arkansas and Mississippi which had very low vaccination rates.  When the wave started Florida stood around #20 in vaccination rates, with rates about equal to or slightly higher than a number of northern states but the Delta wave was much worse than last summer's wave.  Figuring out why this occurred may also help better understand how the virus works. 

Small differences in vaccination rates can lead to large differences in the worst outcomes.  Let's take the UK as a comparison.  65.5% of its population is fully vaccinated and 5.9% partially.  In the US it's 54.5% fully vaccinated and 8.9 partially.  If you look at Covid cases and deaths on a per capita basis, the UK 7-day average is about the same as the US peak of two weeks ago but the US 7-day average death rate is over twice as high as the Brits.  Do the math and it means if you were to scale up the UK population to that of the US, the US is experiencing 1,000 more deaths a day than the UK, which I think primarily attributable to the difference in vaccination rates.

Meanwhile, we'll be getting our flu shots and the covid booster as we are now more than seven months out from our second shots.

Let's hope this is the last big wave before we are left with covid as an endemic virus with occasional larger outbreaks.  As much as I don't like the prospect, this is going to be something we will have to learn to live with at some level.

And if you want to keep up with developments on the story around covid origins read Alina Chan.

Monday, August 30, 2021

COVID + 17

With the Delta variant on the loose, Covid is now global.  As mentioned in the last report South and Southeast Asia, a region only lightly touched by the virus for over a year has, since early summer, become a hot spot.  Malaysia, Thailand, Vietnam, Sri Lanka, Indonesia and Myanmar are each averaging the equivalent of 1,000 to 3,000 deaths a day in the U.S.  For reference the seven-day average for deaths in the U.S. peaked at 3,500 in mid-January 2021 and is currently at 1,060.

Two months ago I felt we were past the worst of covid but am no longer so optimistic.  Actually we are past the worst, I just thought things would continue to improve as they had since the spring.  Two months ago I wasn't wearing a mask when going into a store, now I am.  I know several vaccinated people who have recently got covid, though none ended up in the hospital.  

This piece from Charles Cooke at National Review sums it up, "The Bitter Truth: There's Still No Rhyme or Reason to Covid-19":

Two presidents. Fifty states. One-hundred-and-ninety-five countries. A multitude of different approaches. And still, there’s no rhyme or reason to this pandemic.

A few days ago, the New York Times ran an excellent piece on the terrible spike in Florida. “Even a state that made a major push for vaccinations . . . can be crushed by the Delta variant,” the paper observed, while noting that “Florida ranks 21st among states and Washington, D.C., in giving people of all ages at least one shot.” Indeed, the Times noted, nobody is quite sure why this is happening. “Exactly why the state has been so hard-hit,” it concluded, “remains an elusive question” — not least because “other states with comparable vaccine coverage have a small fraction of Florida’s hospitalization rate.”

Many of the Times’s readers were frightfully upset by this blunt assessment of the facts.

For months, many in the press have banged on and on and on about Florida’s governor and then been shocked to learn that, even after a terrible spike — a spike that, mercifully, is beginning to fade — Florida’s record remains better than those of New York, New Jersey, Massachusetts, Rhode Island, Connecticut, Michigan, and Illinois; that the number of children who have died in Florida (per capita) is not only exactly in line with the national average, but around five times lower than D.C.’s number, and just over half of New York’s; that, far from lagging behind, Florida’s vaccination rate is above the national average; and that, despite having a disproportionately old population, Florida sits in the bottom half for deaths among senior citizens. The state of Louisiana, which seems to get hit around the same time as Florida each time there is a wave of COVID-19 infections, currently boasts many policies that Florida does not — among them, an ongoing indoor mask mandate that applies even to the vaccinated, a statewide school-mask mandate for all students over the age of five, and, in the city of New Orleans, a system of vaccine passports. Despite this, Louisiana’s death rate is the fourth worst in the nation, while Florida — which has a much older population (as of 2020, Florida has the largest senior population in the union; Louisiana’s is 42nd) — sits in 20th place. What gives?

The uncomfortable truth is that, beyond developing, encouraging, and providing inoculation, there’s not much that any government can do to guarantee success — and, even when it does what it can, a lot of people are going to resist for reasons bad and good.  

Given how polarized we are at present, one can easily comprehend why, in its early days, so many political obsessives thought it might be efficacious to use the pandemic as a stick. But now? Eighteen months in? It’s beyond time for them to shut the hell up.

Covid is a virus and it's going to do it's virus thing.  Get vaccinated (isn't it great it became available so quickly?), take reasonable precautions, and hope for the best.  Johns Hopkins maintains a data base of opening and closing decisions by each state along with case trends.  I can't make out much of a connection between those decisions and the disease outcomes.

-----------------------------------------------------------------------------------------

The case against masking children in school.  Matt Shapiro is pretty objective in my view and sets out the reasons for his position.

-------------------------------------------------------------------------------------------

Simpson's Paradox strikes again!  How what looks like lower vaccine efficacy in an amalgamated population can be deceptive.


Simpson's Paradox (about which I wrote several years ago) is when a top line result looks very different from its individual components because of ratio differences between those components.  Here's another recent example related to Covid.  A couple of months ago I noticed that Florida's covid mortality rate was about 10% higher than California's but when I looked in more detail I discovered the death rate in each individual age group was higher in California than in Florida!  What drove the top line difference was that Florida has a much older population than California.

Friday, July 23, 2021

Covid + 16

I usually start these monthly updates with the data on the countries with the highest mortality rates but this month we'll have those at the end of the post because cumulative death rates are no longer the most important covid story.  There are two interrelated stories that need to be emphasized; (1) the covid upsurge in most of Asia and sub-Saharan Africa, and (2) the delta variant.

-----------------------------------------------------------------------------------

The increase in covid cases and deaths noted last month in Asia and Africa has accelerated.  In sub-Saharan Africa there is a shortage of tests, medical care and data but many countries which had been relatively untouched (at least officially) until this May are now facing covid surges.

The same is true in Asia, particularly South and Southeast Asia.  Indonesia is seeing more than 1,000 deaths daily and Myanmar suddenly has a major outbreak.  According to three Indian demographers, that country, which officially reports 420,000 deaths, has actually had in excess of 4 million covid related deaths.

-----------------------------------------------------------------------------------

The delta variant, first identified in November 2020 in India (prior to the use of any vaccines, so claims its origin was prompted by vaccines are not true, is now the predominant strain globally.  It is much more transmissible than earlier variants, though it does not appear more deadly.

For the vaccinated, while the Pfizer and Moderna vaccines are effective against delta, they are not as effective as they are against the original virus and its variants.  However, they are generally effective in reducing the severity of covid-related illnesses.  If you have an immunological compromised system or significant co-morbidities, additional caution is warranted.

For the unvaccinated, particularly the elderly or those with co-morbidities, delta poses an increased risk because of its easy transmissibility, not because it is more severe.

Delta's viral load is about 100x that of the original virus.  One of the implications of this is lowered effectiveness of masking because of the amount of viral aerosolized material emitted by those infected. Masking already had limited effectiveness and that only if the wearer correctly handled the mask; most didn't in my observations.  If you are concerned use N95 masks.

The good news is that given the extent of vaccination so far the increase in cases in the U.S. has not seen as steep a rise in hospitalizations and deaths.  Let's hope that trend continues.

As for what happens next and what you are seeing in the media keep this in mind (from Matt Shapiro's substack, Marginally Compelling):

There is obsession in the press to look at small vaccination differences and treat them like large ones. The United States as a whole is 68.6% vaccinated with at least one dose. The lowest state is almost at 50%, but has still vaccinated 78% of their senior population. When you look at the Kaiser monthly vaccine monitor, you see that almost every variable that raises the risk of COVID (living in a population-dense city, age, having a dangerous co-morbidity) corresponds to a higher rate of COVID vaccination. We’ve targeted the highly-vulnerable and let the medium-vulnerable make their own choices (most have chosen to get vaccinated). As a result, I expect we’re going to start seeing COVID surges that look more like the UK’s recent surge.


Image


-----------------------------------------------------------------------------------

For those in my age group (65+) I support vaccination unless there are medical reasons not to do so, or if you have already had covid.  The age risk factors are enormous as I've previously noted.  I'm glad to see that in Arizona more than 87% of those 65+ have been vaccinated.

If I were a young adult or had children I would be more hesitant about vaccination because the risks associated with these vaccines may outweigh the benefits.  

-----------------------------------------------------------------------------------

Last month I wrote about the China lab leak theory and its plausibility.  Since then it has become even more apparent to me that we should treat it as the default assumption.  China was able within 2-3 months to identify the source of the original SARS viruses back in the 2000s and has had ample opportunity to identify a natural source for covid-19 over the past 18 months and failed to do so.  It now also opposes WHO's recent announcement of a further investigation on the origins of covid-19.  We've learned that more and more of the origin story we were told in early 2020 was wrong - for instance, the first cases were not associated with the Wuhan live market; rather they were close to the Wuhan virology lab.  Our own media helped with the disinformation, peddling the story that the virology lab was sited in that city because it was near the origin point of SARS type viruses.  We now know that the lab was constructed in Wuhan prior to the first SARS outbreak in 2002 and the known sources of the virus are hundreds of miles away; there is no nearby natural source.

-------------------------------------------------------------------------------

Senator Rand Paul lacked discipline in his questioning of Dr Fauci earlier this week but on the big picture he was correct.  Dr Fauci did direct funding to the Wuhan virology lab and it was done so via the EcoHealth Alliance led by the doctor who organized the now inoperative February 2020 letter dismissing a possible lab origin of the virus (which is turn prompted the media to denounce anyone who said otherwise of being guilty of "misinformation" and conspiracy mongering).  Dr Fauci employed his usual tactic of not directly answering questions and, when he does so, using misdirection to let the casual listener think he is responsive when he is not.

Dr Fauci reminds me of another long-tenured DC bureaucrat who amassed too much power and abused it, intimidated those who opposed him, loved the limelight, and could do no wrong in the eyes of his supporters; J Edgar Hoover.  Time for him to go.

------------------------------------------------------------------------------

This week several Democratic senators introduced a bill that would hold Facebook, YouTube and other social media companies responsible for the proliferation of falsehoods about vaccines, fake cures and other harmful health-related claims on their sites.

"The legislation leaves it up to the U.S. Department of Health and Human Services, which is responsible for declaring public health emergencies, to define what constitutes health misinformation."

Has there been misleading and inaccurate information from those opposed to the covid vaccines?  Yes.  But this is a terrible legislative proposal for multiple reasons.

The first is the general principle of freedom of speech which this would violate.

The second is that it delegates the determination of what is "health misinformation" to an agency which has promoted health misinformation in many instances since the beginning of the covid pandemic.  In February of 2020 when Mrs THC and I began to collect face masks, should Facebook have been potentially liable if it failed to prevent us from posting about it at a time when the CDC and Surgeon General said masks were useless?  What about promoting the opening of schools last summer?  What about stating that covid was primarily an aerosol threat, rather than a particle or surface threat?  The evidence of the former was clear by last summer by the official CDC position didn't change until this spring.  

Third is that it allows a government agency to effectively censor America citizens by pretending it is a neutral and objective party.  The school closing issue is a great example.  Its recommendations last year were nonsense but when the CDC was poised to issue new guidance this spring, the teacher unions intervened and, as a major supporter of the Biden administration, were allowed to dictate language eviscerating the policy change.

Finally, this proposal would not be limited to covid information.  In April 2021, the CDC Director declared "racism" a public health emergency.  Does that mean the social media platforms would become liable if someone posted information disputing that declaration and the claims underlying it?  Would Americans be allowed to criticize Black Lives Matter on social media?

The truth is that Progressives and the public health community (which is left-leaning) believe every social problem is really a public health issue in disguise.  If enacted, this legislation would create a channel to effectively bar public discussion of public policy issues under the guise of them being public health issues.  I think those proposing the legislation understand this quite clearly.

The Official Data

Reported below are all countries with population of more than one million which have reported death rates in excess of 1,500 per million (threshold raised from 1,200).

Europe

Hungary (3116), Bosnia & Herzogovina (2968), Czechia (2828), Bulgaria (2639), North Macedonia (2635), Slovakia (2295), Belgium ( 2166), Slovenia (2129), Italy (2119), Croatia (2022)

Poland (1990), UK (1890), Romania (1794), Spain (1736), France (1705), Portugal (1698), Lithuania 1644), Moldova (1551)

North America

USA (1880), Mexico (1823), Panama (1534)

Major Outbreaks: Cuba

South America

Peru (5845), Brazil (2555), Colombia (2290), Argentina (2259), Paraguay (2007)

Chile (1808), Ecuador (1717), Uruguay (1696)

Africa

Tunisia (1511)

Major Outbreaks: South Africa, Namibia, Zambia, Mozambique, Botswana, Zimbabwe, Uganda

Asia

Armenia (1542)

Major Outbreaks: Malaysia, Bangladesh, Indonesia, Iran, Kazakhstan, Thailand, Sri Lanka, Myanmar, Afghanistan

Thursday, June 24, 2021

COVID +15

Covid has moderated in Europe and North America over the past month.  South America continues to have significant problems in most countries and the new trend we noted last month, increases in cases and death in South and East Asia, continues though it has still not reached anywhere near what has occurred in the Western Hemisphere and Europe.  In addition a number of African countries south of the Sahara and north of South Africa are beginning to report higher cases and deaths.

Official v Unofficial Data

Last month I reported on the differences between official and unofficial covid death counts and references the study by The Economist which concluded the likely Covid death toll is slightly above 10 million, or almost triple the official reports.  This month we received some indirect confirmation.  Peru's public health officials completed an exhaustive study of deaths in that country since March 2020 and concluded that covid deaths were more than 2.5x previous reports.  The country adjusted its official death count and it is now 5,717 per million.  Next closest is Hungary at 3,110.  The difference between Peru and Hungary is greater than that between Hungary and the #83 country in the Worldometer tally.  I find it difficult to believe that Peru is such an outlier and that other countries have substantially higher death tolls than being reported.

The Official Data

Reported below are all countries with population of more than one million which have reported death rates in excess of 1,200 per million (I've raised the threshold from 1,000).

Europe

Hungary (3110), Bosnia & Herzogovina (2960), Czechia (2823), North Macedonia (2631), Bulgaria (2613), Slovakia (2289), Belgium ( 2161), Slovenia (2142), Italy (2110), Croatia (2008)

Poland (1982), UK (1877), Spain (1727), Romania (1715), France (1695), Portugal (1680), Lithuania 1629), Moldova (1535)

Sweden (1435), Latvia (1340), Switzerland (1248), Greece (1215), Ukraine (1200)

North America

USA (1858), Mexico (1780), Panama (1482)

South America

Peru (5717), Brazil (2379), Argentina (2005)

Colombia (1996), Paraguay (1659), Chile (1650), Uruguay (1553), Bolivia (1381)

Africa

Tunisia (1207)

Asia

Armenia (1518), Georgia (1313)

--------------------------------------------

On the continuing saga of the origins of Covid 19:

Science Journals, Wuhan and a truly bizarre twitter episode by Matt Ridley 

On the hesitation of some scientists to speak publicly about the Wuhan lab-leak possibility because they would be associated with Trump.  This entire episode has become a disgrace to the scientific community.  Read Alina Chan, a post-doctoral researcher at MIT and Harvard, who took a lot of heat for months on end for just entertaining the possibility of a lab leak.  This is her thread on misinformation regarding the origins of the virus.

Alina has also explained that there is a lot to lose for scientists, especially virologists, if research was the source of Covid-19.
"All at once you’re dealing with your colleagues, institute, reviewers of papers & grants, & the Chinese government.
You’re literally acting against your self interest in every way possible except the interest of not having a future pandemic caused by a research-related accident.
I’ve spoken very highly of sleuths and data analysts who’ve worked on tracing the #OriginsOfCovid but I also need to emphasize that the consequences for scientists are much worse. You could become a pariah overnight, accused of fanning the flames of conspiracy and AAPI hate.  I’m already getting some of it as I tweet. And some well-intentioned people have reached out to me asking wth I’m doing, I have a future that I’m setting on fire. 
When you ask why aren’t more scientists stepping up to call for a credible investigation into both natural and lab origin hypotheses of covid-19, you’re essentially asking why aren’t more scientists also whistleblowers. It’s incredibly excruciating to be a whistleblower. The range of emotions you have to hold on to for months or years, wondering if you’ve got it all wrong and you’re just dragging everyone through a great misunderstanding, exposing your colleagues to threats/danger, jeopardizing your and their careers and happiness.
You cannot ask even 0.01% of scientists to do this. That’s why the search for the origin of Covid-19 has to involve many non-scientists."

From New York Magazine, "The Lab-Leak Groupthink Failure Should Scare Liberals".

A story from Newsweek on the amateur sleuths who investigated the Wuhan lab (Alina Chan gives them a lot of credit for advancing the story).

For those still interested in the myths surrounding the supposed data manipulation by Gov. DeSantis read this piece from PoliMath, The Impossibility of Florida Data Manipulation.  You can read more about the horrible Rebekah Jones, the source of all these false claims, here.